


Most evidence shows TMS does not cause lasting harmful effects when delivered under proper clinical guidelines. For many patients, the more relevant long-term question isn’t about risk, it’s about how long symptom relief actually lasts and whether maintenance sessions might help.
The FDA first cleared TMS for major depressive disorder in 2008, and follow-up research continues to support its long-term safety. For most people, the biggest lasting effect is simply feeling better.
At Center for Psychiatric Wellness, we use NeuroStar TMS, an FDA-cleared platform as part of a personalized psychiatric evaluation process tailored to each patient’s long-term goals. Read on to see what the evidence actually shows about TMS and what to realistically expect after treatment ends.
Key Takeaways
- Most TMS-related side effects, including headache and scalp discomfort, are temporary and go away on their own without any additional treatment.
- Current research finds no evidence of permanent memory loss, cognitive decline, or structural brain damage from TMS when delivered under proper clinical guidelines.
- Long-term success often comes down to a personalized plan, one that may include psychotherapy, medication management, and booster TMS sessions when your provider feels it’s the right call.
What Does the Research Say About Long-Term TMS Safety?
Current research hasn’t found a link between properly delivered transcranial magnetic stimulation (TMS) and permanent brain injury or lasting cognitive problems.
Doctors and researchers have studied TMS in thousands of patients through randomized clinical trials, patient registries, long-term follow-up studies, and real-world treatment programs. At our clinic, we offer NeuroStar Advanced TMS therapy in Fort Smith based on these proven protocols to ensure clinical precision and safety throughout each session.
While researchers have more short-term data than long-term data, the findings have stayed consistent across different patient groups.
The National Institute of Mental Health notes that,
“TMS side effects are generally mild and short-lived when expert guidelines are followed and that most side effects appear to resolve without long-term consequences.” – National Institute of Mental Health.
So far, studies show that TMS has a strong safety record when trained clinicians follow established treatment guidelines.
Researchers continue to track several areas over time:
- Changes in thinking and memory
- Relapse after treatment
- Rare side effects
- Repeat treatment outcomes
- Long-term brain changes
Several brain imaging studies suggest that TMS may change how certain brain networks communicate. These include the default mode network and the frontoparietal network, which help regulate mood, attention, and emotional processing.
Those changes matter.
Current evidence suggests these shifts reflect healthy neuroplasticity, meaning the brain adapts and forms new connections. Researchers haven’t found signs of harmful structural changes linked to clinical TMS treatment.
A key finding appears again and again in published studies: there isn’t consistent evidence that TMS causes permanent brain damage when treatment follows established safety protocols.
Still, long-term research continues. Conditions such as major depressive disorder often last for years, so researchers need extended follow-up to better understand how long symptom relief lasts, how often symptoms return, and which maintenance strategies work best.
TMS Side Effects That Can Last Beyond Treatment
Long-lasting side effects appear to be uncommon, with published safety reviews estimating that serious adverse events occur in fewer than 1% of patients who complete a full TMS course. Even so, some patients report symptoms that deserve medical follow-up.
Most side effects improve during treatment or within days after the final session. But everyone’s experience is different, especially for people who have other medical conditions, medication changes, or ongoing mental health symptoms.
Usually temporary
| Common effects | Less common but monitored |
| Headache | Persistent scalp sensitivity |
| Neck discomfort | Tinnitus |
| Dizziness | Mood changes |
| Jaw or tooth discomfort | Sleep disruption |
The side effects reported most often include:
- Headache
- Scalp discomfort
- Facial muscle twitching
- Neck tension
- Mild fatigue
These symptoms usually improve within a few hours or days after treatment ends. In many cases, simple changes can help reduce discomfort. Clinicians may adjust treatment settings, reposition the coil, recommend short breaks, or suggest over-the-counter pain relievers when appropriate.
Some patients report symptoms that last longer than expected, including ongoing headaches, dizziness, ringing in the ears, or increased sensitivity around the treatment area. Published studies suggest these reports are uncommon, but they shouldn’t be ignored.
Get checked.
Persistent symptoms don’t always mean TMS is the cause. In some cases, symptoms may relate to an underlying psychiatric condition, a medication adjustment, increased stress, poor sleep, or another medical issue.
That’s why follow-up matters.
When Should Persistent Symptoms Be Evaluated?
Contact your treatment team if symptoms continue beyond the expected recovery period or begin to affect daily life.
Medical evaluation is recommended if:
- Symptoms get worse after treatment ends
- New neurological symptoms appear
- Pain affects work or daily activities
- Mood changes become severe or don’t improve
At Center for Psychiatric Wellness, clinicians monitor patients throughout treatment and during follow-up visits. Ongoing assessment helps determine whether symptoms may be related to TMS, underlying mental health conditions, medication changes, or another medical concern.
Don’t wait.
If symptoms persist or interfere with your quality of life, reach out to your treatment team promptly. Early evaluation can help identify the cause and guide the next steps in care.
TMS and Memory Loss: What the Evidence Actually Shows

Current research does not show that transcranial magnetic stimulation (TMS) causes lasting memory loss or long-term cognitive problems.
Memory concerns are one of the most common questions patients ask before starting treatment. In many cases, this worry comes from confusion between TMS and electroconvulsive therapy (ECT).
Although both treatments can help people with depression and other mood disorders, they work in very different ways.
Unlike ECT, TMS:
- Does not require anesthesia
- Does not intentionally trigger seizures
- Allows patients to stay awake during treatment
- Does not cause confusion after sessions
- Has not been linked to persistent memory loss
Most patients can drive themselves to and from appointments and return to work, school, or other daily activities right after treatment.
That’s an important difference.
Large studies, systematic reviews, and meta-analyses consistently report that cognitive side effects from TMS are rare, mild, and short-lived when they occur.
Some patients notice temporary difficulty concentrating because of depression itself, poor sleep, medication changes, or anxiety about treatment. These symptoms often improve as mood symptoms begin to lift.
In fact, several studies have found small improvements in certain areas of thinking, including:
- Attention
- Executive functioning
- Working memory
- Processing speed
Researchers believe these improvements may happen because patients feel less depressed and because TMS changes communication within brain networks involved in mood and cognition. The brain can adapt.
This process, known as neuroplasticity, allows the brain to strengthen or reorganize connections over time. Early research suggests TMS may support these healthy changes, although researchers continue to study the long-term effects.
A key finding remains consistent across studies: current evidence does not support claims that TMS causes long-term memory impairment.
Researchers are also studying TMS in older adults and in people with mild cognitive impairment. Early findings are encouraging, but longer follow-up is still needed before doctors can draw broader conclusions about cognitive benefits beyond mood improvement.
For patients with treatment-resistant depression, early data suggest that cognitive gains may correlate with the degree of mood improvement rather than TMS stimulation alone.
TMS vs. ECT: Key Differences Patients Should Know
TMS and ECT can both help treat depression and other mood disorders, especially when standard treatments have not provided enough relief. Even so, the two treatments differ in several important ways.
TMS uses magnetic pulses to stimulate specific areas of the brain involved in mood regulation. Today, these noninvasive systems are widely known as FDA approved TMS conditions clinical depression and other mood disorders, offering patients a safe and well-tolerated option in an outpatient office setting.
ECT uses controlled electrical stimulation while the patient is under general anesthesia. The treatment intentionally causes a brief seizure under close medical supervision.
Because ECT affects the brain differently, some patients experience temporary confusion or memory problems after treatment. TMS has a more favorable cognitive safety profile.
Patients remain awake during TMS sessions, can communicate with staff throughout treatment, and usually return to their normal routines immediately afterward. Your doctor can help determine which treatment option best fits your symptoms, medical history, and treatment goals.
How Long Do the Benefits of TMS Usually Last?
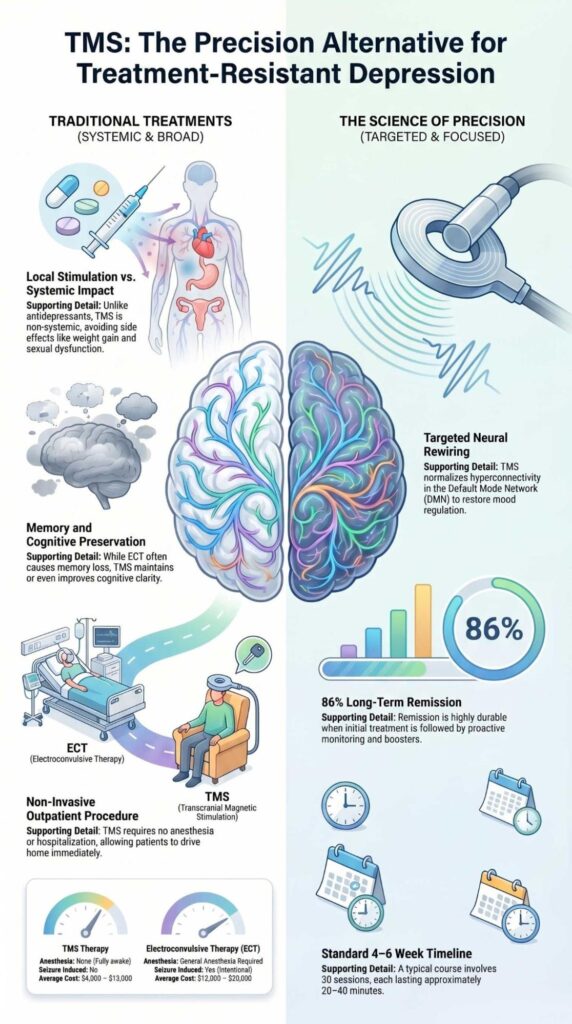
Many patients who respond to TMS continue to feel better for six to twelve months or longer after completing treatment, with some studies reporting sustained remission beyond one year in patients with treatment-resistant depression.
However, symptom recurrence can happen over time. The length of improvement varies from person to person.
Several factors may affect how long benefits last, including:
- Diagnosis
- Severity of symptoms
- How long symptoms have been present
- Other mental health conditions
- Participation in ongoing care
A typical treatment pattern may look like this:
- Weeks 1–6: Initial treatment course
- Months 1–6: Continued improvement
- Months 6–12: Ongoing remission or booster sessions
- Beyond one year: Individualized maintenance planning
Long-term studies of patients with treatment-resistant depression suggest that remission can last for many months after the initial course of TMS.
Still, depression often returns. For many people, depression is a recurring medical condition that benefits from ongoing support, even after symptoms improve. Stopping all treatment after feeling better may increase the risk of relapse.
Combining TMS with other treatments may help patients maintain results over time. These treatments may include:
- Medication management
- Counseling or psychotherapy
- Regular physical activity
- Healthy sleep habits
- Stress reduction strategies
At Center for Psychiatric Wellness, clinicians often combine advanced therapy with medication management, counseling services, and ketamine infusion therapy when clinically appropriate. Treatment plans aren’t one-size-fits-all.
Regular follow-up visits allow clinicians to monitor symptoms, adjust treatment plans, and address early signs of relapse before symptoms become more severe.
Maintenance TMS: Who Needs It and Why It Matters
Some patients notice a gradual return of symptoms after their initial treatment course ends. Maintenance TMS may help extend remission and lower the risk of relapse.
Patients who have experienced multiple depressive episodes often benefit from ongoing monitoring and a personalized maintenance plan.
The goal isn’t to continue treatment forever. The question is, does TMS work permanently?, it depends on individual factors including diagnosis, symptom history, and initial treatment response which is why maintenance plans are built around each patient’s pattern, not a fixed schedule.
For some patients, occasional booster sessions are enough. Others may benefit from a more structured schedule. Your treatment team will review symptom patterns, treatment response, and personal preferences when creating a long-term plan.
Does Maintenance TMS Reduce the Risk of Relapse?
Current evidence suggests that maintenance TMS may reduce relapse rates for some patients. There is no single maintenance schedule that works for everyone.
Common approaches include:
- Weekly sessions
- Sessions every other week
- Monthly booster treatments
- Short retreatment courses if symptoms return
Maintenance recommendations often depend on:
- Initial response to treatment
- Number of previous depressive episodes
- Patterns of symptom recurrence
- Patient preferences
Patients who may benefit the most include:
- People with recurrent depression
- Patients who relapsed after previous improvement
- Individuals who responded well to their initial TMS course
Clinical studies suggest that ongoing maintenance strategies may lower relapse rates compared with no follow-up treatment with some naturalistic studies reporting relapse rates as low as 10 to 20% in patients who continued with scheduled booster sessions.
Even so, maintenance TMS is not necessary for every patient. Some people continue to do well after a single course of treatment, while others need occasional booster sessions to maintain symptom relief. That’s normal.
At Center for Psychiatric Wellness, long-term planning begins before the first TMS session. Patients learn what to expect during treatment, how symptoms are monitored over time, and what options are available if symptoms return.
Patients Who Benefit Most From TMS Maintenance Sessions
Patients with treatment-resistant depression and a history of recurring symptoms often benefit from individualized continuation plans.
People who experienced strong improvement during their initial TMS course, especially those with multiple past depressive episodes, may also benefit from maintenance treatment.
Regular follow-up appointments help clinicians identify early warning signs of relapse and adjust care before symptoms interfere with daily life. The goal is lasting stability, not ongoing treatment for its own sake.
Seizures and Mania: Recognized but Rare TMS Risks

Yes. Seizures and mania are recognized risks of transcranial magnetic stimulation (TMS), but both complications are uncommon.
For most patients, TMS has a strong safety record when clinicians follow established screening and treatment guidelines.
Seizures are the most serious potential complication associated with TMS. Published safety data estimate that seizures occur in about 7 out of every 100,000 treatment sessions.
That’s rare. Even so, seizure risk is not the same for everyone. A patient’s medical history, current medications, and lifestyle factors can affect their level of risk.
The FDA’s own guidance on,
“TMS systems acknowledges seizure as an identified risk, and requires manufacturers to include clear labeling that describes the limitations of available information on the safety and effectiveness of long-term treatment.” –FDA.
Factors that may increase seizure risk include:
- History of epilepsy
- Sleep deprivation
- Substance misuse
- Neurological disorders
- Medications that lower seizure threshold
Before treatment begins, clinicians review these factors carefully to determine whether TMS is an appropriate option.
Mania or hypomania can also occur during treatment, especially in people with bipolar disorder or an undiagnosed bipolar spectrum condition. Published case reviews estimate mood switching occurs in a small minority of patients, most commonly in those with an unrecognized bipolar history prior to TMS.
Symptoms of mania may include increased energy, reduced need for sleep, racing thoughts, impulsive behavior, or unusually elevated mood.
Risk factors for mood switching include:
- Bipolar disorder
- Family history of bipolar disorder
- Previous manic episodes
- Antidepressant use without mood stabilizers
Careful screening matters.
A thorough psychiatric evaluation remains one of the best ways to reduce the risk of mania during treatment.
At Center for Psychiatric Wellness, clinicians review psychiatric history, medication use, neurological conditions, and medical contraindications before recommending NeuroStar TMS.
Patients should continue to report any changes in mood, sleep, energy, or behavior throughout treatment. Early communication allows the care team to adjust the treatment plan if needed.
Mania Risk and TMS: What Bipolar Patients Should Know
Patients with bipolar disorder or a history of mood elevation should discuss these concerns with their treatment team before starting TMS.
People who have experienced manic episodes in the past may need additional monitoring during treatment. Family history also matters, especially when a close relative has bipolar disorder.
Your clinician may recommend changes to medications, closer follow-up visits, or coordination with your psychiatrist before treatment begins. Open conversations help keep treatment safe.
Could TMS Affect Hearing Over Time?

Long-term hearing problems from TMS appear to be uncommon when patients use proper hearing protection.
During treatment, the TMS device produces repetitive clicking sounds. Over multiple sessions, repeated noise exposure could affect hearing if appropriate precautions are not taken. That’s why hearing protection is a standard part of treatment.
Protective measures may include:
- Foam earplugs
- Noise-reducing inserts
- Ongoing monitoring during sessions
Current research has not found evidence of permanent hearing loss associated with routine TMS treatment when patients consistently use hearing protection, a finding consistent with FDA device labeling requirements, which mandate hearing protection as a standard precaution during all TMS sessions.”
A small number of patients report temporary symptoms such as:
- Tinnitus
- Increased sound sensitivity
- Mild changes in hearing perception
These symptoms usually improve after treatment ends and rarely lead to lasting problems. Patients should tell their treatment team about any hearing concerns, especially if symptoms continue between sessions or worsen over time.
Why Does Hearing Protection Matter?
Consistent use of ear protection reduces total noise exposure across the full course of treatment. Even brief periods without hearing protection can increase risk over time. Check before every session.
Patients should confirm that ear protection is provided and fits properly before treatment begins. If earplugs feel uncomfortable or do not stay in place, ask the treatment team for alternatives. Simple steps can make a difference.
The “TMS Dip”: What It Is and When to Take It Seriously
Some patients notice a temporary increase in symptoms during treatment, often around the second or third week. Online support groups sometimes call this experience the “TMS dip.”
Patients may report:
- Increased fatigue
- Emotional sensitivity
- Higher anxiety levels
- Temporary worsening of depression symptoms
Experiencing a temporary setback does not necessarily mean treatment isn’t working. Mood symptoms can fluctuate during the early stages of treatment as the brain responds to stimulation. Many patients continue to improve after this period.
Not everyone experiences a dip. Some patients notice steady improvement from the beginning, while others have ups and downs before they feel better.
The timeline varies from person to person.
| Myth | Fact |
| Feeling worse means treatment failed | Temporary symptom changes can occur |
| Everyone experiences a dip | Many patients never notice worsening symptoms |
| Symptoms always continue | Most patients improve as treatment continues |
Keep your treatment team informed about any changes in symptoms, even if they seem minor.
Early communication helps clinicians determine whether symptoms reflect a temporary adjustment period, changes in medications, life stressors, or another medical concern.
When Should You Contact Your Treatment Team?
Reach out to your clinician right away if symptoms become severe or interfere with daily life.
Prompt medical evaluation is recommended if you experience:
- Suicidal thoughts
- Severe anxiety
- New manic symptoms
- Significant decline in daily functioning
Don’t wait. Your treatment team can review symptoms, assess safety concerns, and adjust your care plan if needed.
Regular communication helps ensure that treatment stays both safe and effective throughout the TMS process.
Who Should Avoid TMS or Take Extra Precautions?
TMS is safe for many people, but it isn’t the right choice for everyone.
Certain medical conditions, implanted devices, and medications can increase the risk of complications or make treatment inappropriate. That’s why a complete medical and psychiatric evaluation is an important first step.
Before treatment begins, patients should share their full health history with their care team.
Be thorough.
Patients should disclose:
- History of seizures
- Bipolar disorder
- Brain injury or structural brain lesions
- Implanted metallic devices
- Current medications and supplements
- Substance use history
Even details that may seem unrelated can affect treatment safety. Changes in sleep patterns, alcohol use, recreational drug use, and recent medication adjustments may also influence risk.
TMS is generally not recommended for people with non-removable conductive metal near the head.
Examples include:
- Cochlear implants
- Deep brain stimulators
- Certain intracranial implants
- Implanted electrodes near the treatment area
- Metal fragments in or around the head
Dental fillings, braces, and most common dental work usually do not prevent treatment, but patients should still discuss any implanted devices with their clinician. Safety comes first.
NeuroStar TMS is not appropriate for every patient with depression. It is not typically used as a first-line treatment for mild depression or for people whose symptoms are well controlled with medication alone.
Clinical trial data submitted to and reviewed by regulatory bodies heavily supports the use of NeuroStar for managing major depressive disorder, obsessive-compulsive disorder, and anxious depression. However, establishing long-term safety always comes down to proper patient selection.
People with a higher seizure risk, structural brain changes, or certain neurological conditions require a careful, comprehensive evaluation before any treatment begins to ensure the risk-to-benefit ratio remains favorable.
Age range For TMS is another factor clinicians assess during screening the FDA has not cleared TMS for patients younger than 15 years old.
The goal is to match the right treatment to the right patient.
What Should Patients Disclose Before Treatment?
A complete medical and psychiatric history helps clinicians determine whether TMS is safe and appropriate.
Patients should tell their treatment team about past hospitalizations, previous mental health diagnoses, current medications, prior treatment responses, and any history of neurological conditions.
Family history matters, too. Information about epilepsy, bipolar disorder, or other neurological illnesses in close relatives may help identify potential risks.
Bring a medication list. Include prescription medications, over-the-counter products, vitamins, and herbal supplements. Some medications can affect seizure risk or interact with an overall treatment plan.
Open communication helps clinicians make informed recommendations and create a safer treatment experience.
Questions to Ask Your Doctor Before Starting TMS
Choosing TMS involves more than deciding whether treatment may improve symptoms. Long-term planning matters.
Before starting treatment, ask your clinician how TMS fits into your overall care plan and what to expect after the initial treatment course ends.
Helpful questions include:
- How long do benefits typically last?
- What factors increase my seizure risk?
- Will I need maintenance sessions?
- How will cognitive changes be monitored?
- What happens if symptoms return?
- Which TMS protocol will be used?
- How will TMS work with therapy or medications?
Patients should also ask about treatment schedules, expected side effects, insurance coverage, and how progress will be measured over time.
Many patients find it helpful to bring a list of concerns to the first consultation or invite a trusted family member to attend the appointment. TMS works best as part of a broader treatment plan rather than as a stand-alone intervention.
At Center for Psychiatric Wellness, clinicians combine NeuroStar TMS with individualized psychiatric care, medication management, counseling services, and ongoing outcome monitoring.
The team also helps eligible patients navigate insurance coverage, including Medicare and Tricare benefits, and provides secure access to a patient portal for communication and health information management.
Why Does Long-Term Planning Matter?
Depression and other mental health conditions often require ongoing care, even after symptoms improve.
A clear long-term plan can help patients recognize early warning signs, reduce the risk of relapse, and maintain progress after treatment ends.
Some patients improve after one course of TMS and need no additional treatment. Others benefit from maintenance sessions, medication adjustments, psychotherapy, or lifestyle changes. There’s no single path.
Regular follow-up visits help clinicians adjust treatment plans based on symptoms, treatment response, and patient goals. The most effective care plans focus on long-term wellness, not short-term symptom relief alone.
Long-Term TMS Effects: What Matters Most?
Current evidence suggests that TMS remains a safe, well-tolerated, noninvasive treatment with no established link to permanent cognitive impairment or structural brain injury.
For many patients, the most important long-term question is not whether TMS causes lasting harm but how symptom improvement can be maintained over time. That shift in focus matters. It moves the conversation from fear to planning, which is exactly where it should be.
Maintenance therapy, booster sessions, psychotherapy, and medication management can all play a role in sustaining remission. No single approach works for everyone, and that’s why ongoing clinical oversight makes a real difference in long-term outcomes.
NeuroStar offers an FDA-cleared treatment option for major depressive disorder, obsessive-compulsive disorder, and anxious depression in appropriately selected patients. When used as part of a structured care plan, it gives clinicians and patients a reliable, evidence-backed tool to work with.
At Center for Psychiatric Wellness, we treat TMS as one part of a bigger picture. Our team serving Fort Smith, Van Buren, and Arkoma, Arkansas combines psychiatric evaluations, medication management, therapy, and advanced interventional treatments like NeuroStar TMS and ketamine infusion therapy to build care plans that support real, lasting recovery.
We don’t believe in quick fixes. We believe in getting it right for each person who walks through our door.
FAQ
Can TMS cause any long-term cognitive effects or memory problems?
No. Long-term TMS safety data consistently shows no negative cognitive effects or memory loss in patients who completed full treatment courses. In fact, many patients report clearer thinking after treatment most likely because their depression lifted. Current research supports TMS as a noninvasive, well-tolerated treatment with no evidence of lasting cognitive harm.
How do doctors prevent depression from coming back after TMS?
Doctors typically prevent relapse by combining continuation therapy with scheduled maintenance sessions, either weekly or biweekly, based on individual needs. how a patient responds after completing their initial course.
Psychotherapy and medication management often support this plan as well. Your provider will review your symptom history and recommend a maintenance schedule that fits your specific clinical needs.
Is TMS safe for older adults or teenagers over the long term?
Research on long-term TMS use in elderly and adolescent populations is still developing, but early findings are encouraging. Older adults with treatment-resistant depression have shown meaningful improvement without serious long-term adverse events.
For younger patients, providers apply extra caution around session frequency and response monitoring. A thorough psychiatric evaluation determines whether TMS is clinically appropriate for each individual.
What happens to the brain long-term after repeated TMS sessions?
TMS promotes neuroplasticity by strengthening synaptic connections and improving communication between key brain networks. Longitudinal brain imaging studies show that repeated TMS sessions can produce lasting changes in resting-state connectivity particularly within the frontoparietal and default mode networks.
These changes help explain why many patients continue to experience mood improvement for months after their final session.
Does stopping TMS suddenly cause withdrawal symptoms?
TMS does not cause physical dependence, so stopping treatment does not produce withdrawal symptoms the way some medications do. However, providers often prefer a gradual tapering schedule because it allows close monitoring for returning symptoms.
If symptoms do resurface after stopping, a retreatment protocol or rescue treatment plan can be discussed with your provider promptly.
References
- https://www.nimh.nih.gov/health/topics/brain-stimulation-therapies/brain-stimulation-therapies
- https://www.fda.gov/medical-devices/guidance-documents-medical-devices-and-radiation-emitting-products/repetitive-transcranial-magnetic-stimulation-rtms-systems-class-ii-special-controls-guidance


